

Transcatheter Aortic Valve Replacement (TAVR), also called Transcatheter Aortic Valve Implantation (TAVI), is a minimally invasive procedure used to replace a diseased aortic valve in appropriately selected patients.
The most common reason for considering TAVR is severe aortic stenosis, a condition in which the aortic valve becomes narrowed and restricts blood flow from the heart to the body. The decision to replace the valve depends on the severity of the disease, symptoms, heart function, age, life expectancy, surgical risk, valve anatomy, and the patient’s overall health.
Current international guidelines emphasize evaluation by a multidisciplinary Heart Team when deciding between transcatheter and surgical valve replacement. The 2025 ESC/EACTS guidelines also place greater emphasis on patient-centred decision-making and specialized valve centres.
At Trinity Hospital & Heart Foundation, Basavanagudi, Bengaluru, patients with suspected aortic valve disease can undergo comprehensive cardiac evaluation to determine whether TAVR, surgical valve replacement, or another treatment approach is appropriate.
TAVR is a minimally invasive procedure in which a replacement aortic valve is delivered through a catheter and positioned inside the patient’s diseased valve.
Instead of removing the existing valve through conventional open-heart surgery, the replacement valve is expanded within the diseased aortic valve and begins regulating blood flow.
TAVR is primarily used for appropriately selected patients with severe aortic stenosis.
The procedure may be particularly useful for patients in whom conventional surgery carries increased risk or when a transcatheter approach provides an appropriate balance of benefits and risks.
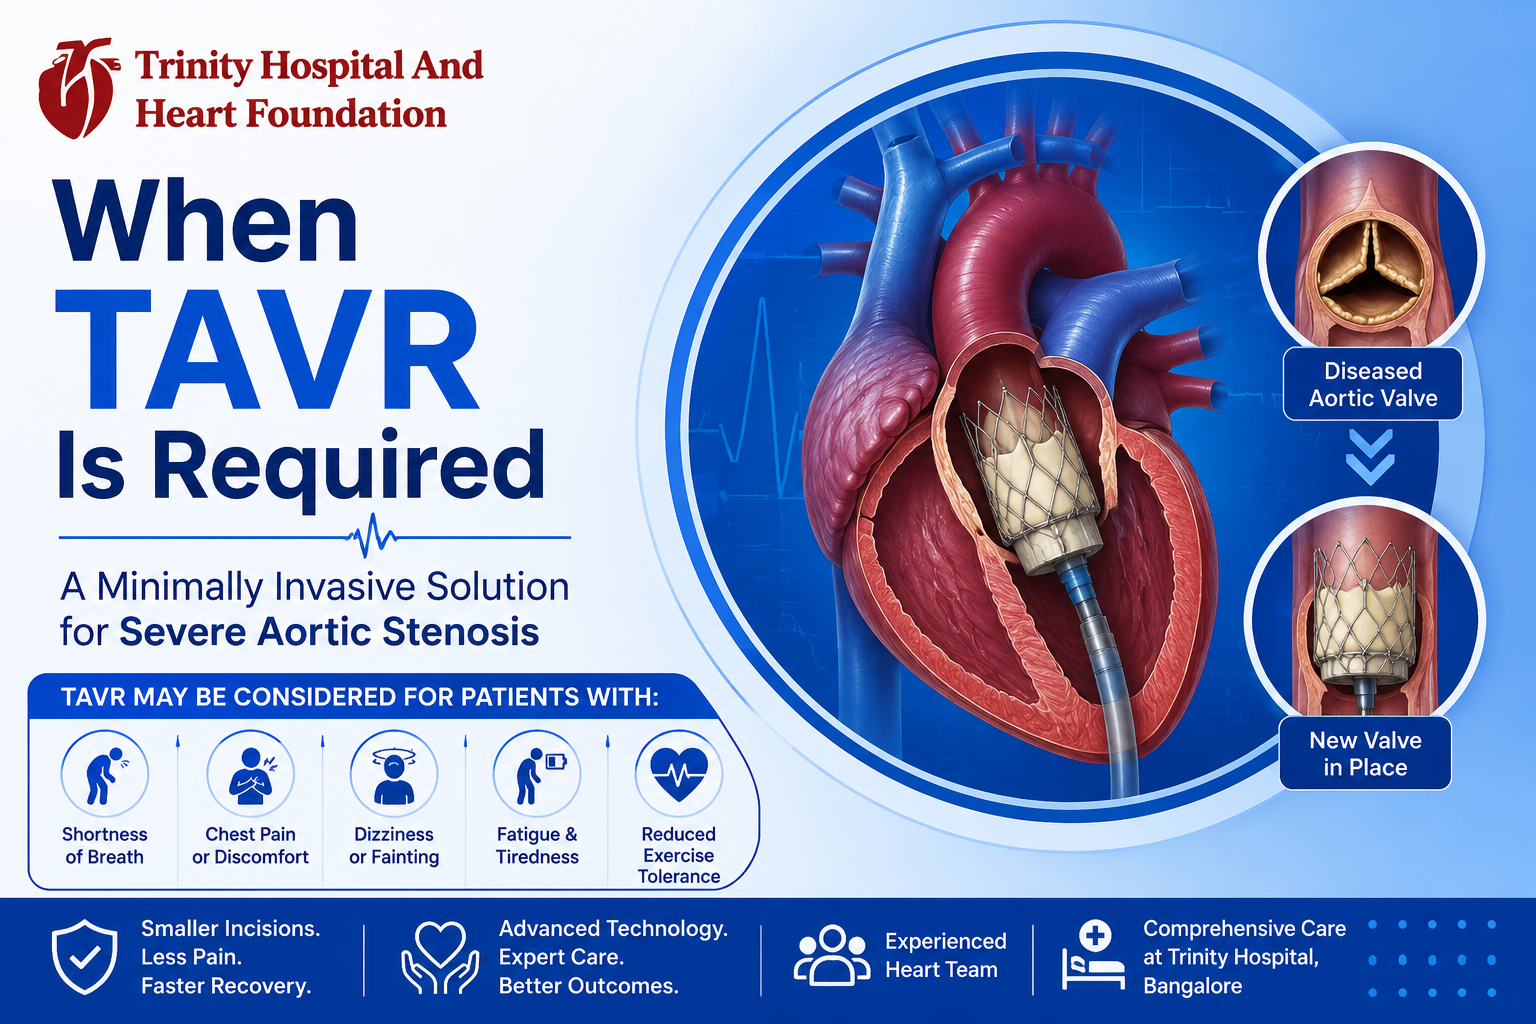
Patients frequently search for what is TAVR surgery because the procedure is sometimes described as “TAVR surgery.”
Technically, TAVR is a catheter-based valve replacement procedure, rather than conventional open-heart surgery.
A catheter is usually introduced through an artery, commonly the femoral artery in the groin, and guided toward the heart. The replacement valve is then positioned within the diseased aortic valve.
The exact access route and procedural technique depend on the patient’s anatomy and medical condition.
TAVR is generally considered when a patient has severe aortic stenosis and valve replacement is indicated.
Important factors include:
The decision is not based on age or symptoms alone. A multidisciplinary Heart Team evaluates the complete clinical picture before recommending TAVR or surgery.
The aortic valve is located between the left ventricle and the aorta. It opens when the heart pumps blood and closes to prevent blood from flowing backward.
When the valve becomes narrowed, the heart has to generate greater pressure to push blood through the smaller opening.
This condition is called aortic stenosis.
As stenosis progresses, the heart may eventually struggle to maintain adequate blood flow. Severe disease can lead to heart failure and other serious complications if appropriate treatment is delayed.
Recognising the symptoms of valve disease is important because severe aortic stenosis may initially cause subtle changes that patients attribute to ageing or reduced fitness.
Common symptoms can include:
Patients may gradually reduce their physical activity without realising that they are compensating for worsening valve disease.
Current European guidance highlights the importance of carefully assessing apparently asymptomatic patients because exercise testing can sometimes reveal symptoms that are not reported during routine history-taking.
There are several causes of valvular disease.
For aortic valve disease, important causes include:
The cause and anatomy of the valve disease can influence which treatment is appropriate.
Degenerative aortic valve disease commonly develops as the valve becomes thickened and calcified over time.
Calcium deposits can make the valve leaflets stiff and reduce their ability to open fully.
As the disease progresses, the opening of the valve can become significantly restricted, resulting in severe aortic stenosis.
Older adults are particularly likely to develop degenerative aortic valve disease, although the exact cause and progression vary between individuals.
Congenital valvular heart disease refers to abnormalities of the heart valve that are present from birth.
One example is a bicuspid aortic valve, in which the aortic valve has two leaflets instead of the usual three.
Congenital valve abnormalities may remain unnoticed for years and can later contribute to valve narrowing or leakage.
Importantly, not every patient with congenital valve disease is automatically suitable for TAVR. Valve anatomy and other individual factors must be carefully evaluated.
What Does a Blocked Heart Valve Mean?
Blocked heart valve is a commonly searched phrase, but it is not usually the formal medical term used by cardiologists.
When a heart valve becomes narrowed and restricts blood flow, the medical term is stenosis.
For example:
Aortic stenosis = narrowing of the aortic valve.
This is different from a coronary artery blockage, where plaque narrows an artery supplying blood to the heart muscle.
The distinction is important because valve disease and coronary artery disease require different diagnostic and treatment approaches.
The heart has four main valves:
They help maintain one-way blood flow through the heart.
Patients sometimes search for valves in arteries, but heart valves should not be confused with valves located inside arteries. The aortic and pulmonary valves are positioned at the exits of the ventricles, controlling blood flow into the aorta and pulmonary artery.
TAVR specifically targets the aortic valve.
Before recommending TAVR, the Heart Team evaluates several aspects of the patient’s condition.
Assessment may include:
An echocardiogram evaluates:
Cardiac CT can provide detailed information about:
An ECG assesses the electrical activity and rhythm of the heart.
Coronary angiography or CT coronary assessment may be recommended when coronary artery disease needs to be evaluated.
Doctors also assess symptoms, physical condition, frailty, other medical illnesses, previous procedures, and expected quality of life.
A diagnosis of severe aortic stenosis does not automatically mean that TAVR is the correct procedure.
Valve replacement may be indicated in severe disease, but the choice between TAVR and surgical aortic valve replacement depends on multiple factors.
The ACC/AHA guidance emphasizes patient age, life expectancy, surgical risk, anatomy, symptoms, and patient preference when selecting between TAVI and SAVR.
The 2025 ESC/EACTS guidelines similarly emphasize individualized assessment by the Heart Team.
The TAVR procedure may be considered for appropriately selected patients with severe aortic stenosis when valve replacement is indicated.
Factors that can support consideration of TAVR include:
However, the presence of any one factor does not automatically make someone a TAVR candidate.
The Heart Team must consider the entire clinical picture.
Patients with severe aortic stenosis who develop symptoms such as breathlessness, chest pain, dizziness, or fainting generally require specialist evaluation for valve replacement.
The ACC/AHA guideline categorizes symptomatic severe aortic stenosis as a stage in which intervention may be indicated, with the choice of procedure depending on patient and procedural factors.
For an individual patient, the Heart Team determines whether TAVR or surgical aortic valve replacement provides the most appropriate treatment.
Age is one of the factors considered when selecting between TAVR and surgical valve replacement, but it should not be viewed in isolation.
According to the ACC/AHA framework, transfemoral TAVI is generally favored in patients older than 80 years or those with a life expectancy below 10 years when the anatomy is suitable, while SAVR is generally favored in patients younger than 65 years or with a life expectancy above 20 years. Patients between these age ranges often require individualized shared decision-making.
More recent European guidance also emphasizes individualized Heart Team decision-making rather than relying solely on age.
A patient’s predicted surgical risk is another important consideration.
Doctors may assess:
Patients at high or prohibitive surgical risk may be considered for a transcatheter approach when the anatomy is suitable and meaningful benefit is expected.
Some patients who have undergone previous cardiac surgery may require another valve intervention later in life.
Previous surgery can make repeat open-heart surgery more complex. In selected patients, a transcatheter approach may therefore be considered after detailed imaging and assessment.
However, previous surgery alone does not mean that TAVR is automatically safer or preferable.
The Heart Team must assess:
One of the most important decisions for patients with severe aortic stenosis is SAVR vs TAVR.
Surgical Aortic Valve Replacement involves surgically accessing the heart and replacing the diseased aortic valve.
It may be preferred in patients who:
TAVR uses a catheter to deliver a replacement valve.
It may be preferred in selected patients who:
The decision should be individualized rather than based simply on the fact that TAVR is less invasive.
The SAVR vs TAVR decision may include:
| Factor | Why It Matters |
| Age | Influences expected valve durability and treatment strategy |
| Life expectancy | Helps determine the long-term value of each option |
| Surgical risk | Estimates the potential risk of conventional surgery |
| Frailty | Helps assess recovery and overall procedural risk |
| Valve anatomy | Determines whether the valve is suitable for TAVR |
| Vascular access | Determines whether transfemoral TAVR is feasible |
| Coronary anatomy | Important for procedural planning |
| Other heart disease | May make surgery more appropriate |
| Previous surgery | Can affect procedural risk |
| Patient preference | Shared decision-making is an important part of treatment |
The 2025 ESC/EACTS guidelines emphasize the role of the Heart Team and specialized valve centres in complex valve disease.
TAVR is not appropriate for every patient with aortic valve disease.
A surgical approach may be preferred when:
For example, TAVR does not directly address all associated cardiac conditions, such as significant disease of other valves or certain aortic conditions.
The causes of valvular disease can influence treatment planning.
For example:
Therefore, identifying the underlying cause is an important part of deciding whether TAVR is appropriate.
Not every patient with severe aortic stenosis has obvious symptoms.
Some people unconsciously reduce their activity to avoid becoming breathless, making the condition appear less symptomatic.
In selected apparently asymptomatic patients, exercise testing and other assessments can help reveal symptoms or identify higher-risk features. The 2025 ESC guidance highlights exercise testing when feasible in patients considered asymptomatic.
Intervention in an asymptomatic patient requires individualized assessment rather than automatically proceeding with TAVR.
Understanding Valvular Heart Disease ICD 10
Patients sometimes search for valvular heart disease ICD 10 when looking for information about diagnosis codes.
ICD-10 coding is used by healthcare systems to classify specific medical diagnoses. There is not one universal ICD-10 code that represents every form of valvular heart disease.
The appropriate code depends on the exact diagnosis, such as:
Therefore, patients should rely on the diagnosis documented by their treating healthcare professional rather than selecting a code based solely on symptoms.
The decision to undergo TAVR should involve more than a single specialist or a single test.
A multidisciplinary Heart Team may include:
The team reviews imaging, symptoms, surgical risk, anatomy, life expectancy, patient preferences, and other medical conditions.
This approach supports individualized decision-making and is emphasized in contemporary international valve guidelines.
For appropriate patients, TAVR can provide:
However, TAVR also has limitations and potential complications. These can include vascular complications, bleeding, stroke, conduction abnormalities requiring a pacemaker, valve leakage, kidney injury, infection, or other procedural complications.
The benefits and risks must be discussed individually before treatment.
At Trinity Hospital & Heart Foundation, Basavanagudi, Bengaluru, patients with suspected severe aortic valve disease can undergo comprehensive cardiac assessment before a treatment strategy is selected.
The evaluation may include:
The goal is to identify the treatment that provides the most appropriate balance of safety, effectiveness, durability, and quality of life for the individual patient.
Medical note: TAVR is not required solely because a patient has aortic stenosis. The indication for valve replacement and the choice between TAVR and SAVR should be determined through specialist evaluation and Heart Team decision-making.
The TAVR procedure is performed in a specialized cardiac catheterization laboratory or hybrid operating room. The exact technique depends on the patient’s anatomy, valve condition, access route, and overall health.
In many patients, the replacement valve is delivered through a catheter inserted into an artery, commonly through the femoral artery in the groin.
The general process includes:
The procedure is planned using detailed imaging to understand the aortic valve, aortic root, coronary arteries, and vascular access.
Before undergoing a TAVR procedure, patients typically undergo a detailed evaluation.
Depending on the individual case, this may include:
The Heart Team uses these findings to determine whether TAVR is appropriate and to plan the safest procedural approach.
One of the reasons TAVR may be considered for suitable patients is that it can avoid the large chest incision associated with conventional surgical valve replacement.
After the procedure, patients are monitored for:
Recovery varies considerably between patients. Age, general health, other medical conditions, complications, and the type of procedure performed can all influence recovery.
Patients should follow their cardiologist’s instructions regarding physical activity, medications, wound care, and follow-up.
Although TAVR is minimally invasive, it is still a major cardiac procedure and has potential risks.
Possible complications include:
The individual risk depends on the patient’s age, anatomy, medical conditions, valve characteristics, and procedural factors.
Before treatment, the Heart Team should discuss the expected benefits and potential risks with the patient and family.
Successful treatment of severe aortic stenosis can improve symptoms and functional capacity in appropriately selected patients.
After TAVR, patients should focus on maintaining overall cardiovascular health.
Important measures include:
TAVR treats the diseased aortic valve, but it does not eliminate other cardiovascular risk factors.
Regular follow-up helps doctors monitor the replacement valve and the patient’s overall cardiac health.
Follow-up may include:
Patients should report new or worsening breathlessness, chest discomfort, fainting, persistent fever, swelling, or palpitations to their healthcare provider.
No.
TAVR is primarily used for appropriately selected patients with aortic stenosis requiring valve replacement. It is not automatically appropriate for every type of aortic valve disease.
The underlying cause is important.
For example, patients with certain forms of:
may require a different treatment strategy.
The Heart Team evaluates the specific anatomy and clinical situation before recommending treatment.
If you experience possible symptoms of valve disease, particularly:
you should seek medical evaluation.
Patients with known severe aortic stenosis should not delay follow-up simply because symptoms appear mild. Some people unconsciously reduce their activity to avoid symptoms.
Patients seeking evaluation for aortic valve disease and TAVR in Bengaluru may travel from:
Trinity Hospital & Heart Foundation is located in Basavanagudi, Bengaluru and can be accessed by public and private transportation.
Nearby landmarks include:
Patients can use Metro services, BMTC buses, taxis, or private vehicles depending on their location.
Aortic valve replacement requires careful assessment rather than a one-size-fits-all approach.
At Trinity Hospital & Heart Foundation, patients can undergo comprehensive evaluation of suspected aortic valve disease, including assessment for TAVR procedure suitability.
The cardiac care pathway may include:
The final treatment decision is based on the patient’s anatomy, disease severity, symptoms, age, health status, procedural risk, expected benefit, and personal preferences.
If you have been diagnosed with severe aortic stenosis or are experiencing breathlessness, chest discomfort, dizziness, fainting, or reduced exercise tolerance, specialist evaluation can help determine whether valve replacement is necessary.
At Trinity Hospital & Heart Foundation, Basavanagudi, the cardiac team can evaluate whether a TAVR procedure, surgical valve replacement, medical monitoring, or another treatment approach is appropriate for your condition.
 24 Hour Emergency Aid